Choosing a therapist can feel personal before you have even said a word in session. You may be sharing experiences you have not told anyone else, so therapist credential verification is not just paperwork. It is one practical way to confirm that a provider has the education, training, and legal authority to offer the care they describe.
Credentials cannot tell you everything about what therapy with a person will feel like. They can, however, give you a grounded place to start. When you understand what to check and what each credential means, you can spend less time guessing and more time finding care that feels right for you.
What therapist credential verification actually means
Therapist credential verification is the process of confirming that a mental health professional is qualified to practice. In most cases, this includes checking their professional license, the state where that license is active, their education, and whether they are permitted to provide telehealth services to someone in your location.
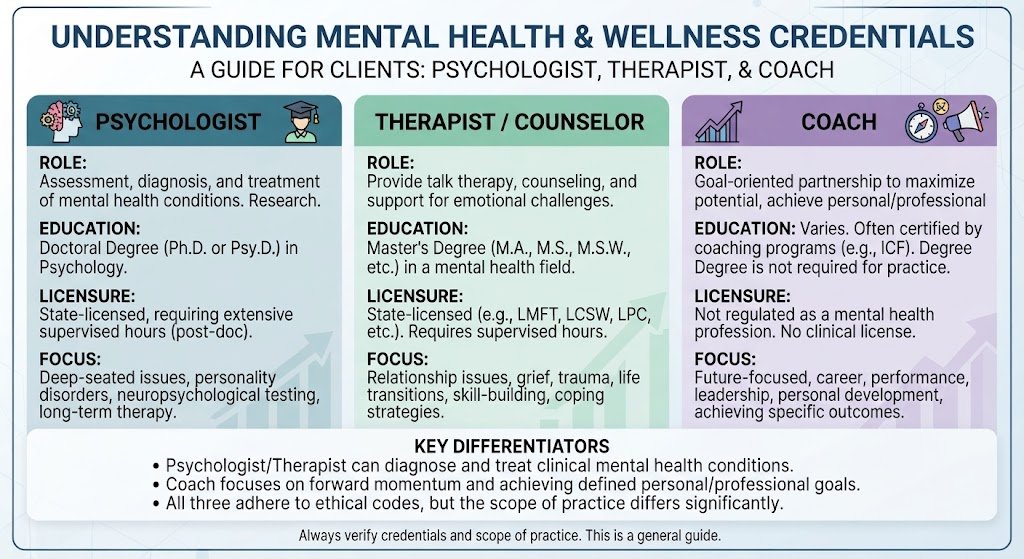
A verified provider should be able to clearly share their full name, professional designation, license type, and the state or states where they are licensed. Depending on their role, you may see letters such as LPC, LMHC, LCSW, LMFT, psychologist, or psychiatrist after their name. These titles reflect different educational paths and scopes of practice.
For example, a licensed clinical social worker commonly holds a master’s degree in social work and clinical licensure. A licensed marriage and family therapist has specialized education in relationship and family systems. Psychologists generally hold doctoral degrees, while psychiatrists are medical doctors who can evaluate medication needs. None of these titles automatically make one provider better than another. The right choice depends on the support you are seeking.
Why verification matters before online therapy
Virtual therapy makes it possible to connect with qualified care from home, which can be especially helpful for people with busy schedules, limited transportation, or few local options. It also means that location and licensing rules require extra attention.
In the United States, mental health licenses are usually issued by states. A therapist may be highly qualified but still may not be able to provide therapy to a client who is physically located in a state where they are not licensed or otherwise authorized to practice. This is generally based on where the client is during the session, not where the therapist’s office is located.
Verification also helps protect you from misleading titles. Terms like “coach,” “counselor,” or “therapist” can be used differently depending on the setting and state. A provider can offer valuable support without holding a clinical license, but they should be transparent about their training, services, and limits. If you are seeking treatment for anxiety, depression, trauma, relationship distress, or another mental health concern, understanding that distinction helps you make an informed choice.
A platform’s screening process can reduce the work you need to do alone. At TheraConnect, provider vetting and thoughtful matching are designed to help clients begin with qualified professionals while still giving them a meaningful choice in their care.
What a thorough verification process should check
The strongest verification process looks beyond a profile photo and a list of specialties. It checks whether a license is current and active, whether the provider is authorized to practice in the relevant state, and whether their listed credentials match official professional records.
It should also consider any public disciplinary history where applicable. A past complaint does not always provide the full story, and clients should avoid making assumptions from a record without context. Still, public licensing information can help you recognize serious concerns, such as a suspended or revoked license.
Education and clinical training matter, too. Graduate programs, supervised clinical hours, and licensing examinations all play a role in preparing a provider for independent practice. Providers may also pursue additional training in areas such as trauma-focused therapy, perinatal mental health, grief, substance use, or couples counseling.
Specialized training can be useful when it aligns with your needs, but it should not be treated as a promise of results. Therapy is collaborative. A clinician’s approach, your goals, the consistency of sessions, and the relationship you build together all affect the experience.
How to review a therapist’s credentials yourself
You do not need to become an expert in licensing regulations to ask clear, reasonable questions. Start by reviewing the provider’s professional title and the state where they are licensed. If something is unclear, it is appropriate to ask directly: “What is your license type, and are you able to see clients who are located in my state?”
You can also ask about their experience with the concern bringing you to therapy. Someone may be fully licensed yet not be the best fit for a specific issue. If you are looking for help with panic attacks, for instance, ask how they typically work with anxiety and what approach they use. If you are navigating a major life change, ask whether they have worked with clients in similar transitions.
Be alert to vague answers about qualifications, pressure to commit before you have your questions answered, or claims that sound too certain. Ethical therapists do not guarantee a cure, promise quick transformation, or present themselves as the only person who can help you. They should be able to explain their fees, cancellation policy, privacy practices, and how they handle urgent safety concerns.
You may also want to ask whether they accept insurance, offer sliding-scale options, or can provide a superbill for possible reimbursement. Affordability is part of access. A therapist who is clinically well qualified but consistently outside your budget may not be a sustainable choice, and that is a valid factor in your decision.
Credentials and connection are both necessary
Verification establishes a baseline of trust. It does not replace the human side of therapy. After your first few sessions, consider whether you feel heard, respected, and able to speak honestly. Notice whether your therapist explains their recommendations in a way you understand and welcomes your feedback.
Sometimes a qualified therapist is simply not the right match. Their communication style may feel too structured or too open-ended. Their availability may not work with your schedule. You may need someone with deeper experience in a particular area, or you may prefer a therapist who shares an aspect of your identity or life experience. Changing therapists in those circumstances is not a failure. It is part of taking your care seriously.
If you have immediate concerns about safety, ethical behavior, or whether a provider is practicing within their scope, pause treatment and seek guidance from the appropriate licensing authority or a trusted health professional. For an urgent mental health crisis, contact emergency services or a crisis resource in your area.
Finding therapy should not require blind trust. Credentials give you evidence that a provider has met professional standards; a good conversation gives you a sense of whether you can work together. Check both, then give yourself permission to choose care that feels qualified, clear, and genuinely supportive. When you are ready, get started with the questions that matter most to you.
For many therapists and mental-health professionals, accepting insurance has been an important way to make care accessible and build a client base.
But insurance participation can also involve contracts, reimbursement requirements, administrative processes, credentialing and network rules.
For some providers, the question eventually becomes:
“Is staying on this insurance panel still the right model for my practice?”
Depaneling from insurance means ending participation with an insurance company’s provider network. A provider may leave one panel while remaining contracted with others, or may eventually transition toward a private-pay or out-of-network practice.
The decision is individual, and the process requires planning.
The American Psychological Association’s 2025 Practitioner Pulse Survey found that 38% of psychologists reported that they did not accept any form of health insurance. Among psychologists who did accept insurance, 10% reported stopping participation in a private or commercial insurance panel during the previous year. Among psychologists who did not accept insurance or had stopped participating in some panels, insufficient reimbursement, administrative issues and payment reliability were among the reported barriers.
What Does Depaneling From Insurance Mean?
Depaneling means a provider terminates participation in an insurance network.
Depending on the provider’s contracts and practice model, this could mean:
Leaving one insurance panel
Leaving several insurance panels
Remaining in-network with selected insurers
Moving toward out-of-network care
Moving toward a private-pay model
Creating a hybrid practice
Depaneling does not automatically mean that every client must immediately stop seeing the provider.
The applicable insurance contract, state requirements and circumstances surrounding the termination matter.
Why Are Therapists Leaving Insurance Panels?
There isn’t one reason.
Every provider has different financial, professional and practice-management considerations.
However, national survey data show that insurance participation can present challenges for psychologists.
In the APA’s 2025 Practitioner Pulse Survey, psychologists who did not accept insurance or had stopped participating in an insurance panel most commonly identified insufficient reimbursement (75%), administrative issues (57%), and concerns about payment reliability (43%) as barriers.
The APA’s 2024 survey similarly found that psychologists in the relevant group cited insufficient reimbursement, administrative issues and payment reliability as leading barriers.
These are survey findings among psychologists. They should not be interpreted as meaning every therapist has the same experience with insurance.
Depaneling Doesn’t Have to Mean Going Completely Private Pay
These terms are sometimes confused.
Depaneling
Leaving participation with a particular insurance network.
Out-of-network
A provider isn’t contracted as an in-network provider with a particular plan. Depending on the client’s insurance policy, out-of-network benefits may still be available.
Private pay
The client pays the provider directly rather than the provider treating the client as an in-network insurance patient.
Hybrid practice
A provider accepts some insurance plans while also serving private-pay or out-of-network clients.
A therapist can therefore make changes gradually rather than necessarily changing the entire practice model at once.
Start With Your Insurance Contract
Before notifying an insurance company, review the agreement.
Look for provisions addressing:
Termination
Required notice
Effective termination date
Existing clients
Claims after termination
Documentation
Credentialing
Provider directories
Post-termination responsibilities
Payment and recoupment provisions
Don’t assume every payer follows the same process.
The contract controls the contractual relationship, subject to applicable law and regulation.
If you’re unsure about your obligations, consider consulting an attorney or qualified healthcare-contract professional.
How Much Notice Is Required?
There is no single notice period that applies to every insurance contract.
Your agreement may specify the required notice and the method by which notice must be provided.
Ask the insurance company to confirm in writing:
That your notice was received.
Your official termination date.
Any remaining contractual obligations.
How existing clients will be handled.
How outstanding claims should be submitted.
When your directory information will be updated.
Keep copies of your correspondence.
What Happens to Existing Clients?
This is one of the most important issues to consider.
A client who selected your practice because you were in-network may face different costs when your network participation ends.
Depending on the circumstances, continuity-of-care protections may apply.
Washington’s Office of the Insurance Commissioner explains that consumers can have continuity-of-care protections when a provider-insurer contract ends, under qualifying circumstances. Washington also has requirements concerning notices about provider-network contract terminations.
Federal continuity-of-care protections under the No Surprises Act may also apply in qualifying circumstances.
Providers should determine which requirements apply to their specific situation rather than assuming that one rule applies to every client.
Washington Providers: Pay Attention to Current Requirements
For therapists practicing in Washington, the state’s provider-network rules are particularly important.
Washington’s Office of the Insurance Commissioner states that state law requires standard notices when certain provider contracts are expiring or being terminated. The OIC provides standard template language for these notices.
The OIC also explains that Washington law provides continuity-of-care protections in qualifying situations when a provider’s contract with an insurer ends.
Requirements can change, so Washington providers should check current OIC guidance and applicable law when planning a network termination.
Talk With Your Clients Before the Change Creates a Surprise
A client shouldn’t ideally discover that your insurance status has changed when they receive an unexpected bill.
Depending on your contractual and legal obligations, consider communicating clearly about:
What is changing?
Explain which insurance relationship is ending.
When is it changing?
Provide the applicable effective date.
What could change financially?
Explain that the client’s insurance coverage and out-of-pocket responsibility may change.
What options might exist?
Depending on the client’s plan and your practice, options could include:
Continuing as a private-pay client
Using out-of-network benefits
Finding another in-network provider
Exploring other coverage
Transitioning to another clinician
Avoid guaranteeing a specific insurance reimbursement amount unless the client’s plan has confirmed it.
Out-of-Network Doesn’t Always Mean No Insurance Coverage
This distinction is important for both providers and clients.
Some insurance plans offer out-of-network benefits. Others may provide little or no coverage for out-of-network care.
The Washington OIC advises consumers to check their individual plan for out-of-network benefits and other cost-sharing requirements.
Therefore:
Out-of-network does not automatically mean uninsured.
Clients should verify their individual benefits directly with their insurance company.
Build Your Referral Strategy Before You Depanel
One of the biggest business considerations is what happens to referrals.
If an insurance directory has been a major source of new clients, leaving that network may change how prospective clients discover you.
Before depaneling, consider developing multiple referral channels:
Your website
Google search
Professional directories
Physician referrals
Therapist-to-therapist referrals
Community organizations
Professional networking
Social media
Educational content
Existing professional relationships
Mental-care directories
The goal isn’t necessarily to replace one referral source with another overnight.
It’s to create multiple ways for potential clients to discover your practice.
Your Online Visibility Matters
When someone is looking for a therapist, they may want to know:
What does this provider specialize in?
Who do they work with?
Where are they located?
Do they offer telehealth?
What types of concerns do they address?
What credentials do they have?
How can I contact them?
Are they accepting new clients?
A clear professional profile can answer those questions before a prospective client ever makes a phone call.
Our Clients Come From Diverse Backgrounds
TheraConnect is designed for people from all backgrounds, identities, life experiences and walks of life who are looking for mental-care support.
There isn’t one type of person who seeks mental-care support.
People searching for a provider may have different:
Cultural and family backgrounds
Ages and stages of life
Personal experiences
Careers and educational backgrounds
Locations and communities
Mental-health concerns
Goals for support
Preferences for care
Interest in in-person or virtual sessions
That diversity matters to providers.
Your practice may be highly relevant to someone who is specifically looking for your specialty, experience, approach or type of care.
A directory can provide another way for those people to discover you.
Your expertise may be exactly what someone is looking for.
Why Provider Discoverability Matters After Depaneling
Leaving an insurance panel can change where clients find you.
That’s why building a strong discovery strategy can be an important part of the transition.
A professional directory profile can provide another place where prospective clients can learn about:
Your credentials
Your specialties
Your services
Your location
Your session format
Your professional website
How to contact you
For a therapist moving toward private pay or a hybrid model, discoverability becomes part of practice marketing.
Don’t Let Leaving Insurance Mean Becoming Invisible
Your practice doesn’t disappear when you leave an insurance network.
Your:
Experience. Credentials. Specialties. Website. Professional relationships. Reputation. Knowledge. Community presence.
all remain part of your practice.
What may change is how people find you.
That is why it can be useful to develop several referral and visibility channels before your insurance relationship ends.
Build a Diversified Referral System
Consider building several sources of new-client discovery.
1. Search
Make your website easy to discover when people search for your specialty.
2. Professional referrals
Build relationships with other healthcare and mental-health professionals.
3. Educational content
Publish useful information related to your areas of expertise.
4. Professional directories
Maintain accurate profiles where potential clients search for providers.
5. Community relationships
Connect with organizations and communities that may refer people to appropriate care.
6. Social media
Use social media to educate and establish your professional presence.
No single source has to carry your entire practice.
Depaneling From Insurance Checklist
Before You Leave
☐ Review your insurance contract ☐ Identify the termination requirements ☐ Determine your effective termination date ☐ Review applicable state requirements ☐ Determine how existing clients will be handled ☐ Review outstanding claims ☐ Determine your post-termination obligations
Client Transition
☐ Identify affected clients ☐ Review continuity-of-care requirements ☐ Communicate changes appropriately ☐ Explain potential changes in cost or coverage ☐ Provide appropriate transition information
Online Presence
☐ Update your website ☐ Review your insurance information ☐ Update professional directories ☐ Review your Google Business Profile ☐ Update social-media profiles ☐ Make private-pay information clear
Referral Strategy
☐ Build professional referral relationships ☐ Improve your website SEO ☐ Create or update professional directory profiles ☐ Publish educational content ☐ Develop community referral relationships ☐ Make your specialties easy to find
Questions to Ask Your Insurance Company
Before completing the transition, consider asking:
What is the required termination notice?
What is my official termination date?
How will affected clients be notified?
Are continuity-of-care provisions applicable?
How should outstanding claims be handled?
Are there post-termination documentation requirements?
When will my provider-directory listing be updated?
Are there additional forms I need to submit?
Are there outstanding credentialing requirements?
Can you provide written confirmation of my termination date?
The Business Side of Going Private Pay
Moving away from insurance isn’t simply a billing decision.
It can change the way your practice operates.
Your marketing, website, referrals and professional visibility may become more important because potential clients may no longer be discovering you through an insurance network.
That can mean putting more attention into:
SEO
Professional directories
Google Business Profile
Referral relationships
Educational content
Community networking
Professional branding
Online discoverability
The objective is to create a practice that can be discovered through multiple channels.
How TheraConnect Fits Into the Transition
TheraConnect is a mental-care discovery directory, not a therapy provider and not an insurance billing platform.
For providers building or expanding a private-pay or hybrid practice, TheraConnect offers another place where prospective clients can discover their professional information.
Your TheraConnect profile can help showcase:
Your professional profile
Your specialties
Your credentials
Your practice information
Your care format, where applicable
Your website
Information potential clients can use when deciding whether to contact you
TheraConnect’s client audience includes people from diverse backgrounds and walks of life who are looking for mental-care
resources and providers.
Your Expertise Deserves to Be Found
You built your practice to help people.
If you’re changing your insurance model, you shouldn’t have to disappear from the places where potential clients are searching.
Get found. Get connected. Help more people.
Join TheraConnect
Create your professional profile and make your practice easier for potential clients to discover.
Depaneling is the process of ending a provider’s participation in an insurance network. A provider may leave one panel while remaining in other networks.
Why do therapists leave insurance panels?
Reasons vary. APA surveys of psychologists have identified reimbursement rates, administrative requirements and payment reliability as commonly reported barriers to insurance participation.
Can I leave one insurance panel but keep another?
A provider may have different contractual relationships with different insurers. Whether you can do so depends on the applicable contracts and requirements.
Can clients continue seeing me after I leave an insurance panel?
Potentially. Continuity-of-care protections may apply in certain circumstances. Providers should review applicable federal and state requirements and their contracts. Washington, for example, provides continuity-of-care protections in qualifying situations.
Can clients use out-of-network benefits?
Some insurance plans provide out-of-network benefits, while others do not. Clients should contact their insurer to verify their specific benefits.
Do I need a referral strategy before depaneling?
It can be useful to establish multiple sources of prospective-client discovery before leaving a network, particularly if insurance directories have historically generated referrals.
Can a mental-health directory help private-pay therapists?
A directory can provide another discovery channel where prospective clients can learn about a provider’s professional information and determine whether the provider may be appropriate for their needs.
Final Thoughts
Depaneling from insurance is a practice transition—not simply a billing change.
Before making the change, understand your contract, determine your obligations, consider affected clients, review continuity-of-care requirements and develop a referral strategy.
Then make sure prospective clients can still find you.
For providers building a private-pay or hybrid practice, visibility matters.
TheraConnect gives providers another place to put their professional expertise in front of people who are searching for mental-care support—including people from diverse backgrounds, experiences and walks of life.
American Psychological Association — 2025 Practitioner Pulse Survey: current insurance participation and reported barriers among psychologists.
American Psychological Association — 2024 Practitioner Pulse Survey: insurance participation and reported barriers.
Washington State Office of the Insurance Commissioner — Provider Network and Contract Negotiations: network changes and continuity-of-care information.
Washington State Office of the Insurance Commissioner — Network Access Filing: provider-contract termination notice requirements and standard notices.
Important: This article is educational content for TheraConnect and isn’t legal, insurance, billing, or clinical advice. Requirements vary by payer, contract, state and individual circumstances.
Body dissatisfaction among children and adolescents is commonplace and has been linked to decreased quality of life, worsened mood and unhealthy eating habits.
I also have firsthand experience with this topic: I am 15 years post-recovery from an eating disorder, and I grew up when people were beginning to widely use social media. In my view, the impact of social media on diet and exercise patterns needs to be further researched to inform future policy directions, school programming and therapeutic treatment.
A recent review found that, as with mass media, the use of social media is a risk factor for the development of an eating disorder, body image dissatisfaction and disordered eating. In this review, social media use was shown to contribute to negative self-esteem, social comparisons, decreased emotional regulation and idealized self-presentation that negatively influenced body image.
Another study, called the Dove Self-Esteem Project, published in April 2023, found that 9 in 10 children and adolescents ages 10 to 17 are exposed to toxic beauty content on social media and 1 in 2 say that this has an impact on their mental health.
Eating disorders are complex mental illnesses that develop because of biological, social and psychological factors. Eating disorder hospitalizations and the need for treatment have dramatically increased during the pandemic.
Some reasons for this include isolation, food scarcity, boredom and social media content related to weight gain, such as the “quarantine15.” That was a reference to the weight gain some people were experiencing at the beginning of the pandemic, similar to the “freshman 15” belief that one will gain 15 pounds in the first year of college. Many teens whose routines were disrupted by the pandemic turned to eating disorder behaviors for an often-false sense of control or were influenced by family members who held unhealthy beliefs around food and exercise.
Researchers have also found that increased time at home during the pandemic led to more social media use by young people and therefore more exposure to toxic body image and dieting social media content.
While social media alone will not cause eating disorders, societal beliefs about beauty, which are amplified by social media, can contribute to the development of eating disorders.
‘Thinspo’ and ‘fitspo’
Toxic beauty standards online include the normalization of cosmetic and surgical procedures and pro-eating-disorder content, which promotes and romanticizes eating disorders. For instance, social media sites have promoted trends such as “thinspo,” which is focused on the thin ideal, and “fitspo,” which perpetuates the belief of there being a perfect body that can be achieved with dieting, supplements and excessive exercise.
Some social media posts feature pro-eating-disorder content, which directly or indirectly encourages disordered eating. Other posts promote deliberate manipulation of one’s body, using harmful quotes such as “nothing tastes as good as thin feels.” These posts provide a false sense of connection, allowing users to bond over a shared goal of losing weight, altering one’s appearance and continuing patterns of disordered eating.
Small steps at home to cut down on social media consumption can also make a difference. Parents and caregivers can create phone-free periods for the family. Examples of this include putting phones away while the family watches a movie together or during mealtimes.
Mindful social media consumption is another helpful approach. This requires recognizing what one is feeling during social media scrolling. If spending time on social media makes you feel worse about yourself or seems to be causing mood changes in your child, it may be time to change how you or your child interact with social media.
June is Men’s Mental Health Awareness Month, and it runs alongside National Men’s Health Month, which many workplaces, clinics, and community groups already recognize. The two share a straightforward purpose: make it easier for men to say what is going on, and easier for the people around them to hear it without flinching.
Men’s mental health is not a June-only subject. The month works more like a door left open. It gives families, friends, and employers a shared reason to check in, and it gives men an opening to bring up something they may have carried quietly for years.
When Is Men’s Mental Health Awareness Month?
June is the month most commonly tied to men’s mental health awareness. Mental Health America recognizes June as Men’s Mental Health Awareness Month, and June is also observed as Men’s Health Month, with organizations such as NAMI marking awareness events during that period.
Men’s Health Week falls on June 14 to 21, which gives the month a natural midpoint for a workplace lunch-and-learn, a team conversation, or a personal check-in with someone who has gone quiet lately.
You may also see November described as Men’s Health Awareness Month, and some sources connect November messaging with men’s mental health. Because organizations do not all align on the same calendar, it is worth checking a specific organization’s own event page before you plan anything around a particular month.
Why a Month for Men’s Mental Health Exists
Awareness months are not meant to rank one group’s struggles above another’s. They exist to close a specific gap. For men, one of the clearest gaps is willingness to reach out.
Research cited by health systems has found that men tend to be more reluctant than women to seek help or treatment for mental health struggles. That reluctance is not a personality trait men are born with. It is learned, reinforced by expectations about how men are supposed to handle pain, and it can change.
A dedicated month gives people a socially acceptable reason to raise the subject first. For a man who has been waiting for someone else to bring it up, that can make all the difference.
What Keeps the Stigma in Place
Stigma rarely announces itself. It shows up in small, ordinary moments that accumulate over years.
The assumption that talking about feelings is a sign of weakness.
The expectation that a man should solve his own problems without help.
Discomfort from friends or family when a man does open up.
The fear of being seen differently at work or in a social circle.
The belief that support is only for people whose problems are serious enough to earn it.
Each of those beliefs makes the next conversation harder. Breaking them usually happens at a smaller scale than people expect. One honest exchange. One friend who does not change the subject. One appointment made without announcing it to anyone.
Men do not always describe distress as sadness. It can surface as irritability, a shorter fuse, restlessness, or a sense of being flat and disconnected. People close to a struggling man often notice changes before he names them himself:
Withdrawing from friends, family, or activities he used to enjoy.
Changes in sleep, appetite, or energy that persist.
Drinking more, or leaning harder on other substances.
Trouble concentrating, or feeling behind on everything.
Talk of hopelessness, or comments about being a burden.
This list is not a diagnostic tool, and it is not a substitute for professional assessment. A licensed provider can help sort out what is actually going on and what would help. If someone is in immediate danger, contact emergency services or a crisis line right away.
How to Start a Conversation With a Man You Care About
The most common worry is saying the wrong thing. In practice, showing up matters more than wording. A few approaches tend to work better than others.
Pick a low-pressure setting. A drive, a walk, or a shared task often feels easier than a face-to-face sit-down.
Lead with what you have noticed, not with a diagnosis. “You seem worn down lately” lands better than “I think you’re depressed.”
Ask one open question and then stay quiet. Silence gives him room to organize his thoughts.
Skip the fixes. Advice offered too early can sound like proof that he should have handled it alone.
Be steady if he brushes you off. Leave the door open and check in again later.
Offer something concrete. Suggesting a specific next step, like helping him look up providers, is easier to accept than a general offer of support.
Waiting for a crisis is not a strategy. Small, repeatable habits do more for mental health than one dramatic overhaul.
Sleep and movement are the foundation, and they are usually the first things to slip when someone is struggling. Regular contact with people who know you well matters too, even when the conversation stays light. Naming what you feel, out loud or in writing, makes it easier to recognize patterns instead of being run by them.
It also helps to separate “I am overwhelmed right now” from “something is wrong with me.” The first is a situation. The second is a story that keeps men from asking for help.
Finding Support That Fits Your Life
Men often delay therapy because they assume it will be expensive, inconvenient, or a poor fit. Modern options reduce most of those barriers. Many providers now offer telehealth sessions, which remove commute time and make it easier to see someone without explaining your schedule to anyone.
TheraConnect is a free online directory that connects clients with licensed mental health providers across the United States. You can search by location, specialty, and session format, and listings include verified licenses, sliding scale options where available, and telehealth availability. Clients use the directory at no cost. If cost has been the reason you put this off, filtering for sliding scale providers is a reasonable first step rather than a last resort.
If you are in crisis or thinking about harming yourself, contact emergency services or a crisis line immediately. A directory is a tool for ongoing care, not an emergency service.
Ways to Take Part This June
You do not need an official event to participate. Some simple options:
Check in on one man in your life who has been quieter than usual.
Share a resource, such as a directory or a local support group, without attaching a lecture to it.
Ask your workplace whether it plans anything for Men’s Health Week on June 14 to 21.
Talk about your own experience with therapy or counseling if you have one. Normalizing it does more than statistics.
Follow up in July. The men who need support in June still need it afterward.
Awareness months fade, and the men who were struggling in June are still struggling in August. The lasting value of Men’s Mental Health Awareness Month is not the calendar slot. It is the habit it can start: checking in, listening without rushing to fix, and treating help as something a man uses rather than something he earns. That habit is worth keeping all year.
Frequently Asked Questions
Is Men’s Mental Health Awareness Month in June or November?
June is the month most commonly recognized, with Mental Health America citing June as Men’s Mental Health Awareness Month and June also observed as Men’s Health Month. November is also described by some organizations as Men’s Health Awareness Month, with mental health messaging included. Because calendars differ, verify details with the specific organization hosting an event.
Why is there a men’s mental health month?
Awareness months target specific gaps rather than ranking anyone’s pain. Research cited by health systems shows men tend to be more reluctant than women to seek help or treatment for mental health struggles. A dedicated month creates a shared reason to raise the subject, which can make it easier for men to speak up and for others to start the conversation.
Is men’s mental health overlooked?
There is a real gap in how often men reach out for support, which is one reason awareness campaigns and dedicated events exist. Whether that gap feels overlooked depends on your community and the resources near you. What is clear is that reluctance to seek help is learned and changeable, not fixed.
What are some examples of stigma men face?
Common examples include the belief that talking about feelings is weak, the expectation that a man should fix his own problems alone, discomfort from others when he does open up, and fear of being seen differently at work. These beliefs build up over time and make each next conversation harder, even when support is available.
How do I find a therapist who is a good fit?
Start by filtering for what actually matters to you: location, specialty, session format, and cost. A directory such as TheraConnect lets you search by those criteria and see verified licenses, telehealth availability, and sliding scale options. If the first provider is not a fit, trying another is normal and not a failure.
f you’ve searched for a therapist and stopped at the price, you’re not alone. Cost is the number one reason people delay getting mental health support. The good news is that therapy fees are more flexible than most people expect, and a few direct questions can save you weeks of guessing.
Here’s how pricing and insurance actually work, and exactly what to ask before you book.
First, understand how TheraConnect works
TheraConnect is a matching site. We connect you with mental health and wellness professionals across the country, but we are not the provider, and we don’t handle billing or set rates.
Every professional listed on TheraConnect decides two things on their own:
Their fee per session
Whether they accept insurance, offer reduced rates, or both
That means two providers with the same specialty can have very different prices. There’s no standard rate, and no “TheraConnect price.” Cost is always a conversation between you and the provider.
How much does therapy cost per session?
Across the U.S., private-pay therapy commonly runs anywhere from around $75 to $250 per session, with wide variation by location, credentials, and specialty. Providers in large metro areas and those with advanced specializations tend to charge more. Newer clinicians, group practices, and community-based providers often charge less.
Many providers also offer sliding-scale fees, which means the rate adjusts based on what you can afford. Sliding-scale spots are limited, so it’s worth asking early.
Who can take insurance, and who can’t
This is the part most people don’t know, and it matters.
Only licensed clinicians can bill insurance. That includes licensed therapists (LMFT, LCSW, LPC, LMHC), psychologists (PhD, PsyD), and psychiatrists. If a provider holds a state license, they may accept insurance, but it’s still their choice. Many licensed therapists don’t take insurance because of low reimbursement rates and paperwork demands.
Coaches and wellness practitioners are private-pay. Life coaches, wellness coaches, and other non-licensed professionals can’t bill insurance. That doesn’t make them less valuable for the right goals, but it does mean you’ll pay out of pocket.
If using insurance is important to you, filter for licensed therapists and psychologists, then confirm directly that they’re in-network with your plan. “Accepts insurance” and “in-network with your specific insurer” are not the same thing.
The two questions to ask every provider
Before you book a first session, ask these two questions. Ask them by email, phone, or during a free consultation call, whatever the provider offers.
1. “What is your fee per session?”
Get the number. Ask whether the first session (often called an intake) costs more, and whether they charge for missed or late-canceled appointments.
2. “Do you take insurance or offer reduced rates?”
If they take insurance, ask which plans and whether they’re in-network. If they don’t, ask about sliding-scale availability or a reduced rate for a set number of sessions. You can also ask for a superbill, a receipt you submit to your insurer for possible out-of-network reimbursement.
If affordability is a concern, say so directly
People often feel embarrassed to bring up money with a therapist. Don’t be. Providers hear this every day, and a good one would rather know your budget up front than have you disappear after two sessions.
Try something simple: “I want to be upfront that cost is a concern for me. Is there a rate that could work?”
The provider might offer a lower rate, suggest biweekly sessions instead of weekly, or refer you to a colleague or community clinic that fits your budget. Any of those answers moves you forward.
Therapy should feel accessible, not out of reach.
Other ways to lower the cost of therapy
Check your Employee Assistance Program (EAP). Many employers cover several free sessions per year.
Ask about telehealth. Some providers charge less for virtual sessions.
Look for training clinics. University counseling programs offer supervised therapy at reduced rates.
Use your HSA or FSA. Therapy with a licensed provider is typically an eligible expense.
Ask about session frequency. Every other week can be effective and cuts cost in half.
How to find a provider on TheraConnect
Search by specialty, location, and the type of support you’re looking for. Each listing shows the provider’s credentials so you can tell at a glance whether they’re licensed (and eligible to take insurance) or a coach or wellness practitioner (private-pay). Then reach out, ask the two questions above, and decide from there.
Browsing is free and no account is needed. When you’re ready to be matched with a provider, you’ll create a free client account so we can connect you.
FAQ
Does therapy take insurance? Only licensed clinicians (therapists, psychologists, psychiatrists) can bill insurance, and each one decides whether to accept it. Always confirm your specific plan is in-network.
How much is therapy without insurance? Private-pay sessions commonly range from about $75 to $250 depending on location and credentials. Sliding-scale rates can be lower.
What is a sliding-scale fee? A reduced rate based on your income or ability to pay. Ask each provider whether they offer one.
Can I use a life coach through insurance? No. Coaches aren’t licensed clinicians, so their services are private-pay.
What should I ask a therapist about cost? Two questions: “What is your fee per session?” and “Do you take insurance or offer reduced rates?”
Finding mental-care support in Michigan begins with identifying your goals and the kind of professional you want to contact. Review provider information carefully and consider practical details such as location, online availability, fees, and scheduling. It is appropriate to ask questions before deciding whether a professional’s services fit your needs.
TheraConnect helps people discover mental-care providers in Michigan by making it easier to explore provider profiles, specialties, services, and locations.
Find a licensed therapist in Michigan with TheraConnect
Find Mental-Care Support in Michigan
You may be looking for support with anxiety, stress, relationships, grief, confidence, burnout, or life transitions. Use profile details to understand each provider’s background and focus areas. Confirm qualifications and scope of practice, especially if you are comparing licensed clinical services with coaching or other forms of personal development support.
Explore Options Around Michigan
Whether you are searching around Detroit, Grand Rapids, Warren, Sterling Heights, Ann Arbor, Lansing, Dearborn, or Flint, use location details to narrow your search when possible. For virtual services, confirm the provider can serve clients located in Michigan and ask about appointment platforms, availability, and fees.
What to Compare When Choosing a Provider
Before contacting a professional, consider these questions:
Qualifications and scope of practice: What license, certification, or training does the professional hold, and what services do they provide?
Area of focus: Does their listed experience match the concern or goal you want to discuss?
Appointment format: Do they offer in-person or online appointments, and can they serve someone located in your state?
Cost: What are the fees? Do they accept insurance where applicable, and are self-pay or sliding-scale options available?
Availability and fit: Do their hours, communication style, and approach fit your needs?
How TheraConnect Helps
TheraConnect is a directory that helps people discover mental-care professionals and review provider profiles. TheraConnect does not itself provide therapy or clinical care. Contact the individual professional to confirm credentials, services, fees, and current availability.
Compare profiles for qualifications, areas of focus, appointment format, location, and cost, then contact providers to confirm current details.
Does TheraConnect provide therapy?
No. TheraConnect is a directory that helps people discover professionals; it is not a clinical provider.
What should I confirm before booking?
Confirm credentials, services, location or online eligibility, fees, and availability directly with the provider.
Take the Next Step
Finding support is a personal process. Review provider profiles, ask questions, and confirm the details that matter to you before deciding on a next step.
Explore other state guides
You can also explore mental-care resources in Illinois and Ohio.
Complex PTSD can develop after prolonged or repeated traumatic experiences. Learn about C-PTSD symptoms, possible causes, how it differs from PTSD, and why trauma-informed mental care matters.
Trauma doesn’t always happen once.
For some people, trauma is a single devastating event. For others, it is repeated or prolonged—sometimes lasting months or years.
It can happen during childhood or adulthood.
Living through ongoing abuse, domestic violence, war, captivity, sexual violence, torture, trafficking, or other repeated traumatic experiences can have lasting effects on a person’s emotional health, relationships, sense of safety, and view of themselves. (Oxford Health NHS Foundation Trust)
One condition associated with prolonged or repeated trauma is Complex Post-Traumatic Stress Disorder, commonly called C-PTSD.
What Is Complex PTSD?
Complex PTSD is related to PTSD, but it is a distinct condition.
The World Health Organization recognizes Complex Post-Traumatic Stress Disorder as a separate diagnosis in ICD-11, the international classification system used for health conditions. (World Health Organization)
C-PTSD can develop following particularly severe, prolonged, or multiple traumatic experiences in childhood or adulthood. Oxford Health gives examples including repeated abuse, torture, severe domestic violence, slavery, and genocide. (Oxford Health NHS Foundation Trust)
That distinction is important.
C-PTSD is not simply “childhood trauma.”
A person can experience trauma at 8, 18, 38, 58, or any other age.
What Can Cause C-PTSD?
No single experience automatically causes C-PTSD.
Possible sources of prolonged or repeated trauma include:
Childhood abuse or neglect
Domestic violence
Repeated physical or sexual assault
War or armed conflict
Torture
Captivity
Human trafficking
Slavery
Repeated exposure to violence
Severe and prolonged interpersonal abuse
The NHS specifically identifies childhood abuse or neglect, ongoing domestic violence or abuse, and repeatedly witnessing violence or abuse among experiences that can be associated with C-PTSD. (nhs.uk)
However, experiencing trauma does not automatically mean someone will develop C-PTSD or PTSD.
People respond to traumatic experiences differently. The World Health Organization notes that most people exposed to potentially traumatic events do not develop PTSD. (World Health Organization)
C-PTSD vs. PTSD: What’s the Difference?
PTSD can occur after experiencing or witnessing a traumatic event or events.
Common PTSD symptoms can include:
Flashbacks
Intrusive memories
Nightmares
Avoiding reminders of trauma
Feeling constantly on guard
Being easily startled
Difficulty sleeping
Anxiety
Feeling disconnected from yourself or the world
These symptoms can sometimes appear immediately or months or even years after the traumatic experience. (nhs.uk)
C-PTSD can include PTSD symptoms plus additional difficulties involving emotional regulation, self-worth, and relationships. (Oxford Health NHS Foundation Trust)
This is one of the major differences between the two conditions.
Common Symptoms of Complex PTSD
C-PTSD can affect people differently, but some common difficulties include:
Difficulty regulating emotions
You may become overwhelmed by anger, fear, sadness, or anxiety and have difficulty calming yourself afterward.
Some people experience the opposite and feel emotionally numb or disconnected.
A negative view of yourself
C-PTSD can involve persistent feelings of shame, guilt, worthlessness, defeat, or feeling fundamentally different from other people. (Oxford Health NHS Foundation Trust)
Relationship difficulties
You may want close relationships but struggle to trust other people.
You might fear abandonment, have difficulty feeling emotionally close to someone, or expect relationships to eventually become unsafe.
Hypervigilance
You may constantly scan your surroundings for danger.
A change in someone’s voice or behavior may immediately put you on alert.
Avoidance
You may avoid people, places, conversations, memories, or situations that remind you of the trauma.
Dissociation or feeling disconnected
Some people experience periods of feeling detached from themselves, their emotions, memories, or surroundings. Dissociation can occur in connection with traumatic experiences. (nhs.uk)
C-PTSD Can Affect Relationships
Trauma doesn’t stay neatly contained in one part of your life.
These behaviors do not automatically mean someone has C-PTSD.
There can be many explanations for these experiences, which is why professional assessment matters.
Why Talking About Trauma Matters
Trauma is more common than many people realize.
The The Conversation article you provided, “More than half of Australians will experience trauma, most before they turn 17. We need to talk about it,” discusses the high prevalence of traumatic experiences and the importance of increasing awareness and conversation around trauma.
The article is particularly useful for highlighting how frequently trauma can occur during childhood and adolescence—but it’s important to remember that trauma isn’t limited to childhood.
People can experience traumatic events throughout their lives.
And some people experience multiple traumatic experiences at different stages of life.
Having C-PTSD does not mean you are permanently damaged.
Treatment can help people understand trauma responses, develop coping strategies, improve emotional regulation, strengthen relationships, and work through traumatic experiences.
Oxford Health notes that treatment may need to be adapted to address difficulties such as emotional instability, dissociation, relationship problems, shame, guilt, and anger. (Oxford Health NHS Foundation Trust)
The NHS also lists trauma-focused therapies, including trauma-focused CBT and EMDR, among treatments used for PTSD. A qualified clinician can determine what approach is appropriate for an individual’s situation. (nhs.uk)
You Are Not Your Trauma
Trauma can change how you see yourself.
It can make you believe you’re broken, difficult, weak, or somehow responsible for what happened.
But experiencing trauma isn’t a character flaw.
And the ways you learned to survive difficult circumstances don’t make you a bad person.
Sometimes behaviors that helped someone survive an unsafe situation can continue even after the danger is gone.
Understanding those patterns can be an important step toward changing them.
Your trauma may be part of your story. It does not have to become your entire identity.
And you don’t have to figure it out alone.
Mental-Care Disclaimer
This article is for educational and informational purposes only and is not a substitute for professional mental-health care, diagnosis, or treatment. C-PTSD can only be properly assessed and diagnosed by a qualified professional. Experiencing trauma does not automatically mean someone has PTSD or C-PTSD.
If trauma-related symptoms are affecting your relationships, work, daily life, or sense of safety, consider speaking with a qualified mental-health professional with experience in trauma-informed care.
Sources
World Health Organization — ICD-11 Clinical Descriptions and Diagnostic Requirements. (World Health Organization)
Meera Atkinson, The Conversation — “More than half of Australians will experience trauma, most before they turn 17. We need to talk about it.”Original article
SEO title: Complex PTSD (C-PTSD): Symptoms, Causes & Trauma Effects
Meta description: What is Complex PTSD? Learn about C-PTSD symptoms, causes, prolonged trauma, PTSD differences, relationships, and trauma-informed mental care.
Doctors and nurses seldom learn in school how to tell a family that their loved one is not going to survive. Yet health care professionals face the immense burden of tragedy, illness and dying in an intensely stressful setting as a routine, ongoing part of their jobs.
Studies show that if current trends continue, the U.S. will see a shortage of 1.1 million registered nurses, 3 million other health care workers and over 140,000 physicians by 2033. A 2022 Mayo Clinic study reported that only 58% of physicians would choose to become a doctor again if offered a chance to revisit their career choice, dropping from 72% from just one year before.
Contribution of a study participant who chose to remain anonymous. CORAL
For nearly two decades, our research group – a team of physicians, researchers, creative arts therapists and writers – has focused on understanding the impact of work-related stress on health care workers. In our experience, almost every health care worker has a story about navigating the times when the weight of the profession is just too much to bear.
To help address this issue, in 2019, with funding from the National Endowment for the Arts, our team established the Colorado Resiliency Arts Lab, or CORAL. Our aim is to use creative arts therapy as an intervention to improve the well-being of health care professionals and to restore their sense of purpose in these demanding work environments.
Read news based on evidence, not tweets or TikToks
As physicians who have worked in critical care and emergency medicine for many years, we think that this incorporation of creativity in health care is vital. The nation’s health depends on the well-being of the health care workforce. We believe that incorporating creativity and the arts as a tool for building resiliency in health care workers could help shift the culture of emotional isolation that health care workers live in.
‘Dancing on a Tightrope’ − work from study participant about balancing a sick child and having to put on a brave face for family and work; feeling ashamed for being tired. CORAL
A challenge long in coming
We as health care workers push ourselves to the limits to learn new ways to enhance human health. The irony is that this often comes at the expense of our own physical, emotional and mental health. We learn to mask emotions and internalize all the negative events we see in health care. But that is unsustainable.
Then came the COVID-19 pandemic, which intensified the stress on health care workers: 3 in 5 physicians reported burnout during the height of the omicron variant in 2022.
A combination of higher job demands, workload, job complexity, job pressure and intensive working time during the COVID‐19 pandemic increased stress among health care professionals and led to emotional exhaustion.
Our focus at CORAL has been on teaching health care workers how to use art-making to effectively process trauma and develop coping mechanisms through expression and community. We invite our participants, who include doctors, nurses, social workers, therapists and researchers, to tap into their authentic vulnerabilities and share stories they would not normally tell by using pen and paper, paintbrushes, guitars, songwriting and movement.
From 2020 to 2023, we carried out six cohorts of our 12-week clinical trial of creative arts therapy interventions involving health care professionals working at least half-time. Participants were randomly assigned to one of four creative arts therapy groups: art, music, dance/movement and writing, with 12 weekly sessions lasting 90 minutes each.
We measured participants’ levels of anxiety, depression, burnout, PTSD and job satisfaction through validated questionnaires and asked the same questions again after the conclusion of the intervention. We also measured those scores in a control group that did not take part in the intervention.
https://www.youtube.com/embed/ihbd3NLLTcI?wmode=transparent&start=0CORAL has been providing arts therapy services for years, but the team’s recent study allows it to measure the healing power of art.
The results were eye-opening. Study participants experienced less burnout and expressed a lower desire to leave their jobs. Burnout scores for anxiety, depression, PTSD and emotional exhaustion decreased by 28%, 36%, 26% and 12%, respectively, in the participants receiving the creative arts therapy intervention. These improvements remained up to one year after the conclusion of the program.
Our findings add to the growing body of evidence that creative arts therapy can be an effective tool for dealing with health care worker burnout across the globe.
We believe that creative art therapy is effective because it allows these health care professionals to be imperfect – freedoms that can be healing in and of themselves. They can use these opportunities to speak the unspeakable through an art form, which becomes a vehicle to help explore and recover from trauma.
This in turn can increase their tolerance for imperfection as well as helping them to feel grace and compassion for themselves and each other. It expands their emotional vocabularies and, in so doing, builds their resilience.
A nurse’s reflection on constantly living in the extremes. CORAL
Remembering what it means to be human
Though the roles of doctors, nurses and other health care professionals are often glorified through terms such as “superheroes” and “guardian angels,” in reality they are human beings who make mistakes and get exhausted too.
The creative process invites them to remember what it means to be human, to be vulnerable. A health care professional picking up a paintbrush for the first time since kindergarten can explore feelings that have been suppressed, memories that have been buried – and even forgiveness for mistakes they may have held onto for years.
‘Rawness Contained,’ by a physician participant of the creative arts intervention study. CORAL
One participant in the CORAL program wrote in their feedback: “When I am given space to unmask and show all sides of who I am, I am creative and engaged. I think more deeply and clearly. I am more willing to take the risks necessary to have breakthroughs. I am a better colleague, mentor, friend, partner, and scientist. When I feel safe and supported, I can be whole.”
In early December, The Wall Street Journal published a feature titled “The Loneliest Generation.”
“Baby boomers,” the article notes, “are aging alone more than any generation in U.S. history, and the resulting loneliness is a looming public health threat.”
When researching the Romantic poets, Amherst College English professor Amelia Worsley discovered that the concept of loneliness didn’t emerge until the late-16th century. It was first used to describe the dangers of straying too far from society – to surrender the protections of town and city and enter the unknown.
To be lonely, according to one 17th-century glossary, was to be “far from neighbours.”
2. New World loneliness
As the first European explorers left their neighbors and ventured across the Atlantic, they didn’t know what they’d find. What awaited them in the New World, University of Southern California historian Peter Mancall writes, was left to the imagination: creatures with heads in their chests, brutes with a single, massive leg and cyclops.
The Pilgrims didn’t encounter any of these monsters. But according to William Bradford, the first governor of Plymouth Colony, they nonetheless needed to contend with “a hideous and desolate wilderness, full of wild beasts and wild men.”
While they had God and they had each other, there wasn’t much else. A Native American raid could wipe out the entire settlement; a single strain of disease could kill off the whole group.
They were – in the earliest sense of the word – unbearably lonely.
Over the centuries, as people grew closer and more connected, the old definition of loneliness slipped away.
“Modern loneliness,” Worsley writes, “isn’t just about being physically removed from other people. Instead, it’s an emotional state of feeling apart from others – without necessarily being so.”
Much of this new form of loneliness seems connected to another world – cyberspace – that opened up at the end of the 20th century.
Like the vast, untouched forests of the New World, the wilderness of the web can be imposing, unsparing and lawless. While there might not be literal monsters, trolls pounce, hackers lurk, governments spy and corporations glean data from your messages, searches and purchases.
Yes, all of human knowledge is at our fingertips. But this has created another problem unique to the internet age: information overload.
University of Nevada, Las Vegas sociologist Simon Gottschalk spent a decade studying the social and psychological effects of new information and communication technologies.
“Our devices constantly expose us to a barrage of colliding and clamoring messages,” he writes. The unending stream of alerts and pings “deteriorates how we approach our everyday activities, deforms how we relate to each other and erodes a stable sense of self. It leads to burnout at one end of the continuum and to depression at the other.”
The overwhelming sea of information creates a sense of being unmoored – tugged in one direction by tweets and advertisements, spun in another by breaking news alerts and email notifications.
At the mercy of these forces, exposed to exploitation, unsure of whom to trust, it’s difficult not to feel small, to feel helpless – to feel alone.
A therapy copay may look manageable until it becomes a monthly bill, and for many people without insurance, the listed self-pay rate can make getting support feel out of reach. Affordable online therapy without insurance is possible, but it usually takes more than choosing the lowest number on a website. The goal is care you can continue, with a qualified therapist who is equipped to help with what you are carrying.
Online therapy can remove practical barriers such as commuting, time away from work, and limited local options. It does not make therapy automatically inexpensive, though. Knowing where costs come from, what questions to ask, and when a lower-cost option is a good fit can help you make a confident decision.
What affordable online therapy without insurance really means
“Affordable” is personal. A graduate student working part-time, a parent managing household expenses, and a retiree on a fixed income may each have very different budgets. A session price that works for one person may be impossible for another. Rather than focusing only on the advertised rate, consider what you can reliably spend on mental health care each month without skipping essentials.
It also helps to think beyond the cost of a single appointment. Therapy works best when there is enough consistency to build trust, identify patterns, and practice new skills between sessions. A lower session fee is valuable, but so is finding a schedule you can maintain. For some people, that means weekly appointments. For others, biweekly sessions, shorter check-ins, or a blended plan with a support group may be more realistic.
The right fit depends on your needs. Someone looking for help with a recent life change may need something different than a person managing trauma symptoms, severe depression, or a long-standing relationship pattern. Be honest about both your budget and the kind of support you are seeking. Those details lead to better matches.
Where lower-cost online care can come from
Many licensed therapists offer sliding-scale rates, meaning the fee is adjusted based on income, financial circumstances, or available appointment times. Sliding scale is not a favor you have to earn. It is a common way providers make room for clients who are paying out of pocket. Availability varies, so it is worth asking directly whether a provider has reduced-fee openings or a waitlist for them.
Some clinicians offer lower rates for sessions held at less popular times, such as weekday mornings or early afternoons. Others provide brief consultations that let you learn about their approach before committing to a first full session. A consultation is not therapy, but it can prevent you from paying for several appointments with someone who is not the right fit.
Group therapy can also lower the cost per meeting while offering meaningful professional support. A well-run group is not a substitute for individual therapy in every situation, but it can be especially helpful for concerns such as anxiety, grief, life transitions, parenting stress, or building coping skills. Ask who facilitates the group, what its purpose is, and whether it is appropriate for your goals.
Training clinics and community mental health programs may offer reduced-cost telehealth sessions with supervised clinicians. These options can be a good choice when cost is the primary barrier. Before enrolling, ask how supervision works, what happens if your needs change, and whether the program can provide referrals for more specialized care.
Finally, a therapist-matching platform can save time by helping you identify providers who offer virtual care and work within your budget. TheraConnect connects clients with vetted mental health professionals, and signing up is free. Sharing your preferences early, including your budget range, helps make the search more focused and less exhausting.
Look for value, not just the lowest session rate
A low price is only helpful if the care is safe, appropriate, and usable. Before booking, confirm that the therapist is licensed or practicing under qualified supervision and can provide telehealth to clients in your state. Licensure rules matter because mental health providers are generally required to be authorized where the client is physically located during the session.
You should also understand the provider’s experience with your concerns. You do not need to diagnose yourself before reaching out. Still, it is reasonable to ask whether they commonly work with anxiety, burnout, relationship challenges, grief, trauma, identity concerns, or whatever brings you to therapy. A therapist should be able to explain their approach in plain language and tell you if another level of care would be more appropriate.
Privacy deserves the same attention. Ask whether sessions use a secure video platform, how records are handled, and what you should do if you lose connection during an appointment. Online therapy can be deeply personal, but it works best when you have a private place to talk and a plan for minimizing interruptions.
Questions to ask before your first appointment
Cost conversations can feel awkward, especially when you are already asking for help. They do not need to be. Clear financial information is part of informed care. Before you schedule, ask what a session costs, how long it lasts, and whether the fee changes after the first appointment.
It is also wise to ask about cancellation policies, payment timing, and whether there are charges for forms, letters, messaging, or missed appointments. A provider may have a reasonable rate but a policy that does not work with an unpredictable work schedule or caregiving responsibilities. Knowing this upfront protects your budget and reduces stress later.
You can keep the conversation simple: “I’m paying out of pocket and need to stay within a set monthly budget. Do you have any sliding-scale availability, lower-fee appointment times, or options that might fit?” The answer may be no, and that is okay. A transparent provider can still point you toward a more suitable option.
Make online therapy sustainable at home
The practical setup matters more than people expect. If possible, choose a regular appointment time and a private location where you can speak freely. Headphones, a charged device, and a backup plan for spotty internet can make sessions feel more secure. If privacy at home is difficult, consider whether a parked car, a private office, or another safe confidential space is available to you.
Between sessions, use the support you are paying for. Keep a short note on recurring thoughts, stressful moments, sleep changes, or questions you want to raise. You do not need to complete homework perfectly for therapy to work. A few honest observations can help your therapist understand what is happening in your daily life and make each appointment more useful.
If the first therapist is not a fit, do not assume therapy itself has failed. Fit can involve communication style, cultural understanding, scheduling, therapeutic approach, and financial reality. It is appropriate to say that you need a different style of support or to request another match. Finding the right person can take time, but it should not require settling for care that feels dismissive or unaffordable.
When lower-cost therapy may not be enough
Affordable care should never mean ignoring urgent needs. If you are in immediate danger, thinking about harming yourself or someone else, or unable to stay safe, call or text 988 in the United States for the Suicide & Crisis Lifeline, call 911, or go to the nearest emergency room. Online outpatient therapy is valuable, but it is not designed for every crisis.
For ongoing concerns that feel intense or complicated, a therapist may recommend more frequent sessions, medication evaluation, specialized trauma treatment, or a higher level of care. That recommendation is not a failure on your part. It is a sign that your needs deserve the right kind of support.
You do not have to prove that you are struggling “enough” before looking for help. Start with the budget you have, ask direct questions, and prioritize a qualified provider who treats your time and circumstances with respect. Check your options, get started with a focused match, and take one practical step toward care that can stay with you.